
Lessons from a billing transition · September 2026
Revenue your dashboard cannot see.
We switched billing platforms in the spring. Nothing errored. Collections fell by a third. This is what we found, what it was worth, and what we would tell another practice owner.
Two-page handout (PDF) → Representative-practice version (PDF) →
What happened
- New billing platform in April. Clean cutover by every vendor measure.
- Deposits down by mid-summer. We blamed payer lag.
- September: we joined the EHR, the billing platform, and the payers' own records — visit by visit, claim by claim, payment by payment.
- The leak was in the seams. No system could see it alone.
The idea that found it: start from the visit, not the claim
Every billing report we owned started with the claim. But a claim is already downstream of the thing that actually happened: a patient sat in an exam room with a clinician. If the visit never became a claim, the claim report shows nothing — not a denial, not a zero, nothing. Zeros do not trend.
So we started at the other end. Every encounter in the EHR became a row, and we followed each one forward through every hand it passed through.
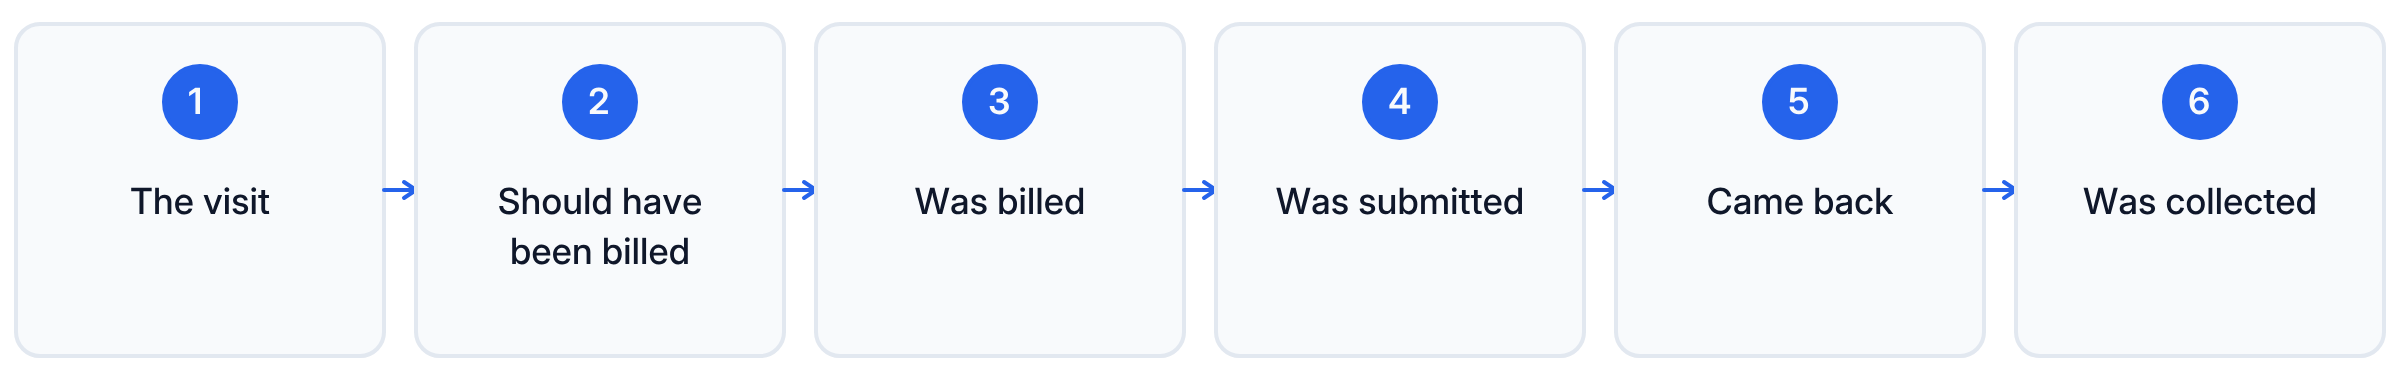
| Hop | Question asked of every visit | Source of truth |
|---|---|---|
| 1. The visit | Did a patient see a clinician? | EHR schedule and signed note |
| 2. What should have been billed | Given what was documented, what was billable? And what else was due and doable that day — the wellness visit the patient was owed, the program they qualified for, the screening one question away? | Note, problem list, care-gap rules |
| 3. What was billed | Was a charge created — right code, unit, provider, place of service, modifier? | Billing platform charge |
| 4. What was submitted | Did the claim leave, and did the clearinghouse and the payer acknowledge it? | Clearinghouse and payer acknowledgements |
| 5. What came back | What was allowed, denied, or ignored, and why? | Remittance |
| 6. What was collected | Was the remit posted, the balance statemented, the denial worked before it aged out? | Posting and A/R |
The visit is the only honest denominator. Hop 2 is the step most reconciliations skip: it asks not only whether everything that happened was billed, but what else could reasonably have happened. In most practices the second number is larger than the first, and it is what turns a recovery project into a plan.
What we found
| Gap found | Claims | Payable (est.) | How it was fixed |
|---|---|---|---|
| Visits that never became claims | 788 | $146k | Claims built from the chart and submitted |
| Program rows never imported (two months) | 1,906 | $109k | Re-import lists handed to the biller |
| Program claims billed at pennies | 591 | $31k | Corrected claims |
| Wrong patient identifiers or payer | 625 | $46k | Corrected in place, biller resubmits |
| Parked at a review gate on a default provider | 99 | $19k | Rendering provider repaired, released |
| A modifier the payer never accepts | 265 | $38k | Modifier removed, corrected claims |
| Out-of-area members sent to the local plan | 292 | $46k | Reroute by member prefix |
| New clinician not yet enrolled | 282 | $47k | Enrollment, then resubmit |
| Total | 4,848 | $482k |
Payable is what the payers' own fee schedules allow on these claims, measured from what the same payers actually allowed on our paid claims of the same kind this year. Collected to date is about $35k, because most of these were fixed in the past two weeks; payer turnaround is 14 to 45 days. We update this as remittances post. The same join looks the other way too: a paid claim the note does not support is flagged for correction and refund exactly as an unpaid one is flagged for resubmission.
Check your own practice this week
- Visits vs claims, per provider per week. More than 3% short is a dropped feed.
- Roster vs claims for each program month. Should match within a handful.
- Paid under a tenth of charge. Unit errors and wrong codes live there.
- "Needs review" older than seven days. Read the oldest ten.
- Same denial, same payer, every month. That is a rule, not a mistake. Fix it once.
Had a transition — billing platform, EHR, clearinghouse, a new clinician or tax id — in the last year? Run all five with the cutover date as the split. If any of them turns up something, it is worth a full pass.
The offer
We are looking for the first few practices to do this with.
We connect read-only to your EHR and billing system under a business associate agreement, match every visit to a bill, every bill to a claim, every claim to a payment, and hand your billing team a list of every gap with the fix for each — plus the second ledger: what was due and doable and not done. Your biller approves every change. You keep every list.
- No fee for the analysis and the report.
- Nothing changes in your systems on our authority.
- Two hours of your billing lead's time, total.
- If you want ongoing help afterward, that is a separate conversation.
Both papers — our own account and the representative-practice version with the full six-hop specification — go to your inbox when you submit.